Pharmaceutical Career Guide
Explore pharmaceutical industry jobs, salaries and career paths across discovery, clinical development, regulatory affairs, manufacturing and commercial. Get interview preparation and stay current on approvals, trials and drug pricing.
How we research our career guides
The Top Pharma News, in 5 Minutes.
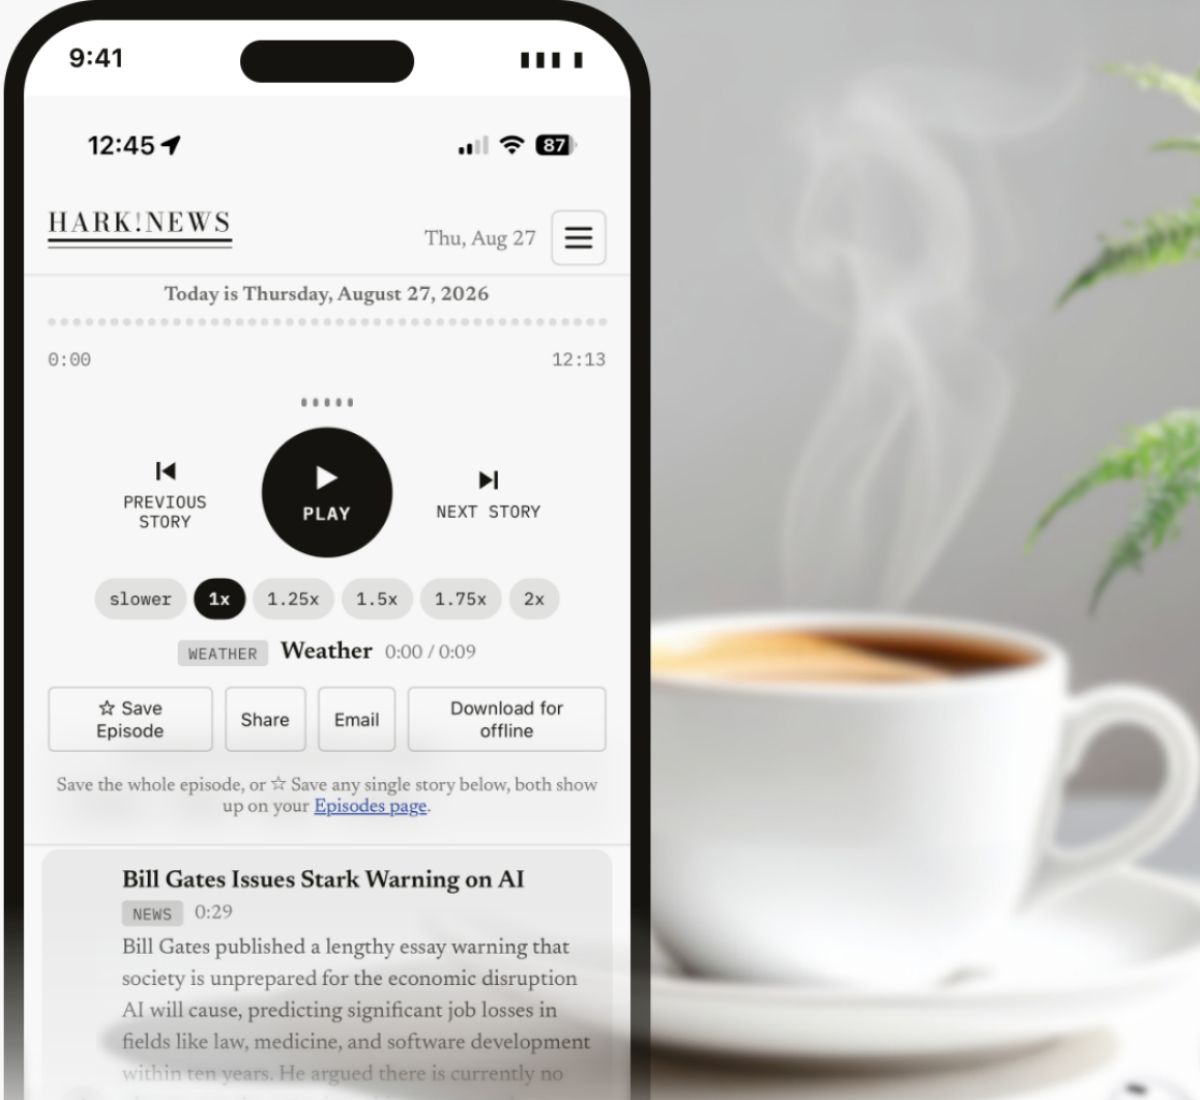
We handpick the best pharmaceutical industry newsletters and distill the readouts, approvals, deals and pricing decisions into a 5-minute audio briefing, delivered by text every morning.
Try Our Pharma BriefingFreeSee the 4 newsletters we handpicked

At a glance
The Pharmaceutical Industry at a Glance
Federal statistics do not record a pharmaceutical occupation, so the industry has to be read across several codes: 181,000 medical scientists at a median of $103,410, 93,500 chemists and materials scientists at $95,060, 74,400 biological technicians at $57,510, 35,200 biochemists and biophysicists at $127,410, 252,100 industrial production managers at $126,060 and 112,200 natural sciences managers at $167,220. The common picture of the industry, a chemist at a bench, covers a narrow slice of it. Most pharmaceutical work is the machinery around a molecule: clinical operations staff who run the trials, data managers who define and clean the endpoints, medical writers who assemble the submission, regulatory affairs professionals who negotiate with the agencies, process development and CMC scientists who make the drug at scale, quality staff who own the systems that keep it lawful, pharmacovigilance teams who collect and assess safety reports, medical science liaisons who talk to physicians, and market access specialists who argue the price. Pay follows scope rather than seniority, and the highest medians belong to people leading the work rather than running the assays. Entry is usually a bachelor's degree, with doctorates concentrated in discovery and translational science, and the industry takes people arriving from clinical practice, statistics, law and the factory floor. The direction of travel is set outside any one company: what regulators accept as evidence, and what payers will fund.
Key Industry Statistics
46
Novel drugs FDA's CDER approved in 2025US Food and Drug Administration
$103,410
Median annual pay, medical scientists (May 2025)US Bureau of Labor Statistics
6 to 10 months
FDA review clock once an application is filedUS Food and Drug Administration
33%
Phase 2 drugs that advance to phase 3US Food and Drug Administration
Common roles
- Clinical Research Associate
- Regulatory Affairs Manager
- Medical Science Liaison
- Clinical Data Manager
- Process Development Scientist
- Quality Assurance Manager
Where the work happens
- Large pharmaceutical companies
- Contract research organisations
- Contract manufacturers
- Generics and specialty makers
- Regulatory agencies
- Consultancies and medical communications
Credentials that matter
- RAC-Drugs
- ACRP certification
- PhD, PharmD or MD
- Project management certification
- Quality and audit credentials
Key Areas in the Pharmaceutical Industry
Discovery & Medicinal Chemistry
Finding and optimising compounds against a target, from screening hits to a development candidate.
Preclinical & Toxicology
Laboratory and animal work under good laboratory practice that establishes dosing and toxicity.
Clinical Development & Operations
Designing, running and monitoring trials through phases one to three, auditably and on time.
Regulatory Affairs
Owning the submission, the agency relationship, the label and the commitments that follow approval.
Manufacturing & Quality
Making the drug reliably at scale under CGMP, and proving it to inspectors.
Medical Affairs & Commercial
Scientific exchange with physicians, plus launch, pricing and market access for an approved product.
Pharmaceutical Jobs & Salaries
Six federal occupation codes cover most paid work inside the industry. They are not one ladder: technicians, scientists and managers are counted separately and entered differently, and the highest median belongs to people leading the work rather than running the assays. Pay is the national May 2025 median.
Biological technicians
$57,510
Chemists and materials scientists
$95,060
Medical scientists
$103,410
Industrial production managers
$126,060
Biochemists and biophysicists
$127,410
Natural sciences managers
$167,220
Source: US Bureau of Labor Statistics, Occupational Outlook Handbook, May 2025 wage data, accessed October 2026.
Pharmaceutical Career Paths
Pharma is not one ladder. It is four tracks that share a pipeline and then diverge sharply in what they own, what they pay and how close they sit to the molecule itself.
- Clinical Trial Assistant0 to 2 yearsTrial master file, site correspondence and tracking. Measured on completeness, not judgement.
- Clinical Research Associate2 to 6 yearsMonitor sites on the sponsor's behalf: source verification, deviations, and whether a site can be trusted.
- Clinical Trial Manager6 to 10 yearsOwn one study end to end, including vendors, budget and the enrolment forecast you have to defend.
- Director, Clinical Operations10 or more yearsA portfolio of studies and the people running them. Judgement about feasibility rather than about sites.
Credential that fits ACRP certification, CCRC for sites or CCRA for monitoring
There is no federal occupation code for a clinical research associate, a regulatory affairs manager or a medical science liaison, which is why the pay table on this page uses the science and management codes instead. Pharmaceutical selling is counted under sales representatives, wholesale and manufacturing, a 1,571,400-job occupation at a median of $76,460 projected to show little or no change to 2035, where pharmaceuticals sit in the technical and scientific products group.
A Typical Day in Pharmaceutical Jobs
Five roles that carry much of the industry's headcount, ordered from a first laboratory job to a function lead. The schedules are representative rather than universal: therapeutic area, company size and trial phase move everything.
Research AssociateEntry-Level · DiscoveryBench work against a target, and the notebook that makes it count for anything later.
- 08:30Read yesterday's plates, flag anything that disagrees with the expected curve before setting up again.
- 09:30Assay setup. Most of the skill is reproducibility, so the protocol is followed rather than improved.
- 12:30Notebook written up contemporaneously, because retrospective entries are what audits find.
- 14:00Team meeting on the series: which compounds advance, which are dropped, what gets made next.
- 16:00Second run, plus the housekeeping on reagents and equipment logs that nobody thanks you for.
Clinical Research AssociateMid-Level · Clinical OperationsMonitoring trial sites on the sponsor's behalf, which means being the person who finds the problem.
- 08:00Prepare for a monitoring visit: open queries, last report's actions, the subjects you intend to review.
- 09:30On site. Source data verification against the case report forms, and the consent files first.
- 13:00Sit with the coordinator on protocol deviations and the ones that need reporting upward.
- 15:30Drug accountability and temperature logs, which is where the unglamorous findings come from.
- 17:00Write the visit report while it is fresh. A late report is a finding of its own.
Regulatory Affairs ManagerMid-Level · RegulatoryThe product's filings, the agency correspondence, and the commitments that outlive the approval.
- 08:30Check the agency portal and the commitment tracker for anything with a date attached this month.
- 10:00Draft a response to an information request, chasing the clinical and CMC inputs it depends on.
- 13:00Review promotional material against the label, because a claim the label does not carry cannot ship.
- 15:00Read a new guidance properly and write the half-page on what it changes for this product.
- 16:30Submission planning: who owns which module, and which date is genuinely at risk.
Medical Science LiaisonSenior-Level · Medical AffairsScientific exchange with specialists in a territory, inside promotional rules that are enforced.
- 07:30Prepare for two appointments: recent publications, the physician's own trial involvement, open questions.
- 09:30First meeting. Non-promotional discussion of the data, including where it is weak.
- 12:00Log the interaction and route any unsolicited request to medical information rather than answering off label.
- 14:00Investigator-initiated study conversation, and an honest view of whether it will be supported.
- 17:00Write up field insights that the medical plan needs and that no other function collects.
Director, Clinical OperationsSenior-Level · Function LeadA portfolio of studies, the people running them, and the forecasts other functions plan against.
- 08:00Portfolio review: enrolment against plan for every active study, and which forecast you now disbelieve.
- 10:00Vendor governance with a contract research organisation, on quality metrics rather than invoices.
- 12:30One to ones. Retention is the number this job is actually judged on.
- 14:30Programme team, defending a timeline to regulatory and commercial with the assumptions exposed.
- 16:30Inspection readiness review on the study closest to filing, file by file.
JOB SEARCH
How to Get a Pharmaceutical Industry Job in 2026
Whether you are leaving the laboratory for industry, moving between functions, or deciding whether the next step is a programme or a department, the questions change with the stage. Pick your level.
Entry-Level
Break Into the Pharmaceutical Industry
What the pipeline is, which functions take people with no industry record, how much education you actually need, and the two standards your work will be measured against from the first week.
What you should know about the field
The shape of the pipeline, what each entry route requires, and the regulations that govern how work is recorded.
What the development pipeline actually looks like
Preclinical work establishes dosing and toxicity in vitro and in vivo before anything reaches a person, under good laboratory practice regulations that govern study conduct, personnel, facilities, protocols, standard operating procedures, reports and quality assurance oversight. Then three trial phases: phase 1 in roughly 20 to 100 participants over several months for safety and dosage, phase 2 in up to several hundred patients over several months to two years for efficacy and side effects, and phase 3 in 300 to 3,000 patients over one to four years.
Learn those numbers early, because almost every job in the industry is defined by which of those boxes it sits in and which document it hands to the next one.
Entry is a bachelor's degree far more often than a doctorate
The federal data is explicit about this and it contradicts the folklore. Biological technicians and chemists both show a bachelor's degree as typical entry-level education. Natural sciences managers also show a bachelor's, plus five years or more of related experience. The doctorate requirement is real but narrow: it applies to medical scientists and to biochemists and biophysicists, which is discovery and translational science rather than the industry as a whole.
So the honest reading is that a doctorate buys you a lane, not the building. If you want clinical operations, regulatory affairs, quality or commercial, three years of real work will do more for you than three more years of study.
The functions you can enter, and what each one owns
Clinical operations splits between coordinators who run trial activity at a site under a principal investigator and monitors who supervise trials on the sponsor's behalf, which the Association of Clinical Research Professionals treats as two separate credentials for exactly that reason. Regulatory affairs owns the submission and the agency relationship, and the Regulatory Affairs Professionals Society counts quality assurance, quality control, approval-linked clinical research and health product project management as adjacent experience that qualifies you for it.
Commercial is the fourth door. The Bureau of Labor Statistics groups pharmaceutical selling under technical and scientific products, where a bachelor's degree is the normal requirement rather than the exception, and the whole promotional side sits under an FDA office that reviews advertising and promotional labeling to confirm it is truthful, balanced and not misleading.
GLP and GCP are the two acronyms you will be judged on
Good laboratory practice is a regulation, cited by FDA at 21 CFR 58.1, setting minimum requirements for how a preclinical study is run and recorded. Good clinical practice is its clinical equivalent: FDA issued ICH E6(R3) as final guidance in September 2025 through its drug and biologics centres, revising GCP around quality by design, risk-based quality management and proportionality, with sponsor and investigator responsibilities clarified.
The practical consequence for a new joiner is that nothing you do counts unless it is documented the way the standard expects. Work that happened but cannot be shown to have happened did not happen.
Skills employers look for
What a hiring manager checks on someone with no track record, beyond the degree itself.
Documentation that survives an audit
Contemporaneous, attributable, legible and complete. The good laboratory practice regulations name written protocols, standard operating procedures, study reports and quality assurance oversight as requirements rather than good habits, and that posture carries through every regulated function in the industry.
Protocol and SOP literacy
Data handling and endpoint discipline
Scientific writing for a regulated reader
Interview questions and answers
Questions new entrants actually get, and what the panel is listening for underneath them.
Walk me through how a drug gets from a target to a label.
What they are looking for: Whether you know the stage gates and the documents, not whether you can recite biology. They are testing industry literacy.
Preclinical work establishes toxicity and dosing, then phase 1 looks at safety and dose in a small group, phase 2 at efficacy and side effects in a few hundred patients, phase 3 at efficacy in up to three thousand. The sponsor then files a new drug application with everything from preclinical through phase 3 plus proposed labeling, FDA decides whether to file it, and the label itself is negotiated with the agency.
Make it yours: Name the documents, not just the phases. Candidates who say IND, protocol, clinical study report and label sound like they have worked here; candidates who only say phase one, two, three sound like they read a diagram.
Why the industry rather than academia or the clinic?
What they are looking for: A reason that survives contact with the work: scale, timelines, teams, regulated rigour. They are screening for people who will leave in a year.
In the lab I liked the experiment and disliked that nothing I did reached anyone. Here the constraint is not curiosity, it is evidence that a regulator will accept, and I would rather work on the version of a question that has a patient at the end of it, even if that means working inside a protocol somebody else wrote.
Make it yours: Be specific about what you are leaving and honest that you are trading autonomy for reach. Answers built on pay or stability read badly even when they are true.
Tell me about a time someone else checked your work and found a problem.
What they are looking for: Whether you can be corrected without defending, and whether you fixed the system or only the instance.
A supervisor reviewing my notebook found I had recorded two incubation times from memory at the end of the day rather than as they happened. I corrected and annotated the entries, then moved to writing times down on a bench sheet in the moment. The second part is what mattered: the first error was carelessness, repeating it would have been a process failure.
Make it yours: Pick a real finding, however small, and spend most of the answer on the change you made. An answer with no finding in it reads as someone who has never been audited.
A monitor finds a consent form signed after the first study procedure. What now?
What they are looking for: That you escalate rather than tidy, and that you understand this as a participant-protection issue rather than paperwork.
I would stop and document what I found, report it to the principal investigator and the sponsor as a deviation, and notify the review board according to the protocol and our standard operating procedure. I would not alter the form. Then I would look at how the sequence was allowed to happen, because the fix is in the site workflow, not in that one file.
Make it yours: Say the word deviation and say who you tell. Any answer that starts by making the file look right is disqualifying.
Mid-Level
Build Depth in One Function
Where the pay actually sits, what the review clock does to your plans, which credentials are recognised, and why quality carries more authority than its grade suggests.
What you should know at this stage
The economics of each function, the agency's own timetable, and the certifications that are worth the fee.
Pay tracks function and scope, not years served
The May 2025 medians run $57,510 for biological technicians, $95,060 for chemists and materials scientists, $103,410 for medical scientists, $126,060 for industrial production managers, $127,410 for biochemists and biophysicists and $167,220 for natural sciences managers. The spread inside the laboratory is narrower than the step into managing the people in it.
Growth does not follow pay. Medical scientists are projected up 13 percent to 2035 and biochemists 12 percent, while industrial production managers grow 3 percent on far larger headcount. A plan built only on the median ignores how many doors will actually be open.
What the submission clock actually is
Once FDA accepts a new drug application for filing, the review team has six to ten months to reach a decision; an incomplete application can be refused filing before that clock starts. Priority review compresses the agency's goal to acting within six months. Reviews are split by discipline, with medical officers and statisticians on the clinical data and pharmacologists on the animal work, each with supervisory review above them, and a project manager assembling the action package that becomes the official record.
The output of all that is smaller than most people expect: FDA's drug centre approved 46 novel drugs in 2025, meaning medicines never before approved or marketed in the United States. Every section you draft is read by a specialist who reads nothing else all day, and very few of those packages become a product.
The credentials that are actually recognised
Regulatory affairs has one: the Regulatory Affairs Certification, with separate RAC-Drugs and RAC-Devices designations. Eligibility is a bachelor's plus three years of regulatory or regulatory-related experience, a master's plus two, a doctorate plus one, or ten years of experience with no degree at all. Clinical research has a family of them from the Association of Clinical Research Professionals: CCRC for coordinators, CCRA for monitors, CPI for investigators, the broader ACRP-CP, and project management and medical device specialties that require you to be certified already.
Neither is a hiring requirement. Both are the cheapest available proof that you learned the rules deliberately rather than by absorption.
Quality is a legal standard, not a preference
Current good manufacturing practice requires systems that assure the proper design, monitoring and control of manufacturing processes and facilities, so that a drug's identity, strength, quality and purity can be relied on. If a company does not follow it, FDA considers any drug it makes adulterated under the law, whether or not that particular batch is defective. FDA inspects manufacturing facilities worldwide, including makers of active ingredients as well as finished products.
That is why quality roles carry authority disproportionate to their pay grade, and why an inspection finding is a company event rather than a departmental one.
Skills employers look for
What separates someone running a workstream from someone being given one.
Running a study to a timeline you defend
Reading a guidance document properly
Cross-functional influence without authority
Risk-based thinking you can write down
Interview questions and answers
Questions about delivery, judgement and compliance, where the subject is the study rather than you.
Tell me about a study or a submission that slipped.
What they are looking for: Whether you saw it coming, what you escalated, and whether you learned something transferable rather than blaming a vendor.
Enrolment at four sites ran at about half the assumed rate by month three. I flagged it at the programme meeting with the projection rather than the shortfall, proposed opening two additional sites and loosening one exclusion criterion, and we took the amendment. We finished about seven weeks late instead of five months late. The learning was that my feasibility assumptions came from the sites with the best answers.
Make it yours: Give the number, the decision and the residual delay. An answer where the slip was entirely somebody else's fault reads as someone who will not tell you early next time.
How do you decide whether something is a reportable deviation?
What they are looking for: A method and a bias toward reporting. They want to know you will not quietly absorb a problem to protect a timeline.
I check the protocol and the standard operating procedure first, then ask two questions: did it affect participant safety, and did it affect the reliability of the data. If either is yes or unclear, it goes up. I would rather over-report and be told the threshold than make that call alone, because the cost of a missed one lands at inspection, not on me.
Make it yours: Name the two tests and say what you do when it is ambiguous. Hedging on ambiguity is the part interviewers listen for.
Describe a disagreement with a cross-functional partner over evidence.
What they are looking for: Whether you argue from the data and the guidance rather than from seniority, and whether the relationship survived.
Commercial wanted a secondary endpoint framed as a benefit in a draft communication. I could show the analysis was not powered for it and that promotional material has to be truthful and balanced and not misleading. We agreed to describe it as exploratory and to fund a properly powered study. The useful move was bringing the regulatory constraint rather than my opinion.
Make it yours: Make the evidence the protagonist. Answers where you won because you were more senior do not travel.
How would you prepare a team for an unannounced inspection?
What they are looking for: Routine rather than heroics. The right answer is that preparation is continuous, because the visit is not scheduled.
The honest answer is that you cannot prepare in the week. What you can do is keep the trial master file complete on a rolling basis, run periodic self-audits against the questions an inspector would ask, and make sure every person who might be interviewed can explain their own task and where the procedure for it lives. Then on the day it is logistics, not archaeology.
Make it yours: Say that the preparation is the operating state. Describing a sprint tells them their files are not current.
Senior-Level
Lead a Function or a Portfolio
The pathway choices, the pricing regime, the safety infrastructure and the AI credibility argument, which are the four things senior pharmaceutical careers are now built on.
What you should know at this stage
Four external forces that senior roles are accountable for, each of which has moved in the last two years.
Expedited pathways reshape the whole development plan
FDA runs four programmes for serious conditions: fast track and breakthrough therapy to speed development and review, accelerated approval, and priority review, where the agency's goal is to act within six months. Accelerated approval allows approval on a surrogate endpoint, a marker such as a laboratory measurement or imaging result expected to predict clinical benefit, and the company must still run studies to confirm that benefit; confirmation converts to traditional approval, and failure triggers procedures that can remove the drug from the market.
Orphan designation runs alongside, carrying tax credits for qualified clinical trials, exemption from user fees and potentially seven years of market exclusivity. Choosing between these is a senior decision with consequences for every function.
Price is negotiated now, and it reaches the portfolio
The Medicare Drug Price Negotiation Program selected 10 Part D drugs for its first cycle, with maximum fair prices effective 1 January 2026, then 15 more Part D drugs effective 1 January 2027, and a third cycle of 15 drugs covered under Part B and Part D plus one drug for renegotiation, with prices beginning in 2028.
The career consequence is that market access stopped being a launch activity. Payer and policy judgement now sits upstream in indication selection and lifecycle planning, which is why commercial and medical colleagues are in portfolio reviews that used to be clinical and regulatory only.
Safety surveillance is being rebuilt around one system
FDA's adverse event reporting infrastructure is consolidating: the public dashboard now runs as the FDA Adverse Event Monitoring System, formerly the FDA Adverse Event Reporting System, and the agency is bringing reporting across drugs, devices, vaccines, tobacco, food, cosmetics and veterinary medicines into one place, alongside consumer complaints and regulatory misconduct reports. Industry, healthcare professionals and consumers all submit.
If you own pharmacovigilance, assume your case intake, coding and signal workflows will be touched by that consolidation, and that the people who read the change early will set their organisation's position on it.
The regulators have told you how to justify an AI model
FDA's January 2025 draft guidance on the use of artificial intelligence to support regulatory decision-making for drug and biological products sets out a risk-based credibility assessment framework for establishing that a model is credible for a particular context of use. It is a Draft Level 1 guidance and explicitly non-binding. On 14 January 2026 EMA and FDA jointly issued ten guiding principles for AI in medicines development, spanning early research, clinical trials, manufacturing and safety monitoring, and applying to developers and to marketing authorisation applicants and holders.
That creates a role. Somebody has to own the credibility argument, and it is neither the data scientists nor the reviewers.
Skills employers look for
What a company is buying when it hires a senior person rather than an experienced one.
Owning an evidence argument end to end
Agency interaction you can be trusted with
Inspection and audit leadership
Interview questions and answers
Senior questions, where the subject is the portfolio, the agency and the decision you would not take.
How would you build a development plan around an accelerated approval?
What they are looking for: Whether you treat the confirmatory obligation as part of the plan rather than a later problem, and whether you can defend the surrogate.
I would start from whether the surrogate is genuinely expected to predict clinical benefit and whether the agency has accepted it in this setting before. Then I would resource the confirmatory trial so it is enrolling at or near the time of approval, because the alternative is holding a licence with no path to converting it and procedures that can take it away. The commercial plan has to assume that risk is visible to payers.
Make it yours: Tie the confirmatory trial to the approval date explicitly. Plans that treat it as a post-launch commitment are how programmes end up in withdrawal discussions.
A confirmatory trial misses its primary endpoint. What do you do in the first week?
What they are looking for: Sequence and candour. They want to see regulatory notification, internal containment and a position formed from the data rather than from hope.
Lock the dataset and get the analysis independently checked before anyone briefs anyone. Inform the agency, and align medical, regulatory, commercial and communications on one factual account. Then do the real work: whether any prespecified subgroup or secondary analysis supports a narrower question worth testing properly, and whether the honest answer is that this indication is finished.
Make it yours: Put verification before communication and say so. Senior interviewers are listening for whether you would brief a board from an unchecked number.
How would you justify using an AI model in a regulatory submission?
What they are looking for: Whether you know a framework exists and can apply it, rather than describing the model. This is a current and deliberately hard question.
I would follow FDA's draft framework: state the question of interest and the context of use, assess the risk the model carries given its influence on the decision and the consequence of being wrong, then plan and document a credibility assessment proportionate to that risk. I would also hold the plan against the joint principles EMA and FDA issued, and keep the whole argument in one artifact with a named owner.
Make it yours: Use the phrase context of use and say the guidance is draft. Candidates who claim it is settled law lose credibility faster than those who have not read it.
How do you decide which programme to stop?
What they are looking for: A stated basis, and evidence you have actually done it. Portfolio leadership is mostly subtraction.
I look at whether the evidence has moved the probability of technical success, whether the indication still clears the access bar given where price negotiation is going, and what the next two years of spend buys versus the same money elsewhere. Then I write the recommendation down with the numbers in it, because a stop decision taken in a conversation gets relitigated for a year.
Make it yours: Name a programme you stopped and what it cost you internally. Answers that only describe a framework suggest you have never carried one.
Why Pharmaceutical Professionals Need to Stay Informed
Approvals, trial readouts, agency guidance and payer decisions all arrive from outside your company, and all of them reset your plan. Staying current is how you see a competitor's miss, a changed evidence standard or a pricing decision in time to act on it rather than react to it.
Read more
The second reason is structural. Restructuring, site closures and portfolio resets are reported in the trade press weeks before they reach an org chart, and the people who move early are the ones who were reading.
The bottom line
The Industry Is Stable. Its Employers Are Not.
The occupations pharma draws on are projected to grow between 3 and 13 percent to 2035, while any single programme can end on one readout. A career here is built on skills that move between companies, and on reading the field before your own employer does.
Stay Informed with Hark's Pharma Briefing
How it works
Pick the newsletters you want
Choose from our handpicked list, or add your own. See the picks
We subscribe you properly
Each one arrives at your own private Hark address, never your inbox.
We read them so you do not have to
Every issue is distilled into one short script each morning.
You listen on the way in
A text arrives with a link. Five minutes, then you are current.
The 4 Pharma Newsletters We Handpicked
BioPharma Dive Daily Dive
Industry Dive
- Free
- Weekdays
- 206k readers
Industry Dive's free weekday briefing on biotech and pharma, tracking clinical trials, FDA actions, and dealmaking for people inside the industry.
Why pharmaceutical professionals read it
Industry Dive's free weekday briefing tracking clinical trials, regulatory actions and dealmaking for people inside the industry, read by more than 200,000 of them. It is the most complete daily view of the sector and the natural anchor here.
More about this newsletter
BioPharma Dive is Industry Dive's free weekday briefing on biotech and pharma: clinical trial readouts, FDA actions, and dealmaking, written for people inside the industry. Its advertising page claims 206,000 newsletter subscribers. The accessible end of the biopharma trade press.
Best for: Biopharma professionals who want a free weekday briefing on clinical trial readouts, FDA actions, and dealmaking written for people inside the industry.
Fierce Pharma / Fierce Biotech
Questex
- Free
- Daily
Long-running flagship free daily on pharma and biotech industry news.
Why pharmaceutical professionals read it
The long-running flagship daily on pharma and biotech industry news. Its commercial coverage, on launches, marketing and manufacturing, runs deeper than the science-first sources, which is why it earns a slot alongside them.
More about this newsletter
Fierce Pharma and Fierce Biotech are the long-running flagship dailies of the drug-industry trade press, covering pharma marketing, manufacturing, clinical results, and biotech financing each weekday morning. High volume and comprehensive. The default inbox presence for industry professionals.
Best for: Industry professionals who want comprehensive, high-volume daily coverage of pharma marketing, manufacturing, and biotech financing every weekday morning.
See the other 2 newsletters
Endpoints News
Endpoints News
- Freemium
- daily
Daily biotech and pharma industry news: drug development, FDA decisions, deals, and the business of medicine.
Why pharmaceutical professionals read it
A daily on drug development, agency decisions, deals and the business of medicine, written for an industry audience. It tends to carry the reporting on financing and strategy that determines which programs continue.
More about this newsletter
Endpoints News is a dedicated biopharma newsroom whose daily emails track drug development, FDA decisions, and dealmaking with wire-service speed and real sourcing. The core newsletters are free; deeper reporting sits behind an Endpoints subscription. A must-follow for anyone serious about the drug industry.
Best for: Drug industry followers who want wire-service speed and real sourcing on drug development, FDA decisions, and dealmaking from a dedicated biopharma newsroom.
The Readout
STAT (Boston Globe Media)
- Free
- Weekdays
STAT's free weekday morning newsletter on the science, politics, and money driving biotech, written by STAT's biotech reporters.
Why pharmaceutical professionals read it
STAT's free weekday morning newsletter on the science, politics and money driving biotech, from reporters who cover the field full time. It is the strongest of these on the science itself and on how policy will treat it.
More about this newsletter
The Readout lands every weekday morning with a rundown of biotech news: clinical readouts, FDA decisions, deals, and market moves, linking to STAT's reporting. The signup page currently credits reporters Meghana Keshavan and Elaine Chen. The newsletter itself is free, though some linked stories sit behind the STAT+ paywall.
You May Also Like
- Biotech ProfessionalsBiotech covers the same science from the other side of the balance sheet: smaller companies, readout-dependent financing, and the cell and gene therapy manufacturing bottleneck that large pharma now buys into.
- PharmacistsDispensing, clinical pharmacy and the licensure route, a separate profession from this one even though both live around the same molecules. Read it if you are weighing a PharmD.
- DoctorsPhysicians are the audience medical affairs speaks to and the investigators who run your trials, so this is a useful read on how the other side of the protocol thinks.
- Health Tech ProfessionalsDigital health, clinical data platforms and the software side of trials, which is the most common route out of pharma for people who prefer the systems to the science.
Frequently Asked Questions
Entry-Level
What does a pharmaceutical professional actually do day to day?
It depends entirely on which box of the pipeline you sit in, which is why the job title matters more here than the industry name. A research associate runs assays and records them; a clinical research associate visits trial sites and verifies source data against the case report forms; a regulatory affairs manager drafts agency responses and checks promotional claims against the label; a quality professional owns whether a facility is defensible to an inspector. What they share is that almost every output is a document somebody else will audit, and that the work is sequenced by stage gates rather than by your own calendar.
Is the pharmaceutical industry a good career in 2026 and beyond?
On the federal projections, the occupations it draws on are all growing: medical scientists 13 percent to 2035, biochemists and biophysicists 12 percent, chemists and biological technicians 7 percent each, natural sciences managers 8 percent, industrial production managers 3 percent. The caution is that the sector is stable while individual employers are not, because a programme can end on one readout and restructuring follows pipeline resets. Treat it as a good industry with volatile employers, and build the kind of function-specific skill that moves to the next company without renegotiation.
How do you get your first job in the pharmaceutical industry?
Three doors open most often. Laboratory roles, where a bachelor's degree is the typical entry-level education for biological technicians and chemists. Clinical operations, usually via a trial assistant or site coordinator post, which is why the Association of Clinical Research Professionals maintains a separate coordinator credential. And regulatory or quality support, where the Regulatory Affairs Professionals Society explicitly counts quality assurance, quality control and approval-linked clinical research as qualifying experience. Contract research organisations and contract manufacturers hire at volume and are the least credential-bound starting point, which makes them the usual first employer rather than the brand you have heard of.
What is the difference between pharma, biotech and a contract research organisation?
Large pharma owns a marketed portfolio and runs discovery through commercial under one roof, so roles are narrower and the process is heavier. Biotech is usually earlier, smaller and financed against readouts, so roles are broader and employment is tied more tightly to a single programme. A contract research organisation or contract manufacturer sells capability to both: you run other companies' trials or make other companies' products. The work is often the same work, but the CRO route gives you more studies and more therapeutic areas faster, at the cost of owning none of them.
Do you need a PhD or a PharmD to work in pharma?
No, and the federal data is unusually clear on it. A doctoral or professional degree is listed as the typical entry-level education for medical scientists and for biochemists and biophysicists, which is discovery and translational science. Biological technicians, chemists and even natural sciences managers show a bachelor's degree, with the managers also needing five years or more of related experience. A doctorate buys you a particular lane rather than the industry, and a PharmD or MD matters most in medical affairs. For clinical operations, regulatory, quality and commercial, experience and a recognised certification go further.
Which degrees and entry-level titles lead into drug development?
Life sciences, chemistry, pharmacy, nursing, statistics and engineering all feed in, and the degree matters less than the first title you can get. The entry titles that lead somewhere are research associate, clinical trial assistant, clinical research coordinator, regulatory affairs associate, quality assurance associate, medical information associate and manufacturing or laboratory technician. For the commercial side, pharmaceutical selling is classified under technical and scientific products, where a bachelor's degree is the normal requirement. Pick the title closest to the function you want, because moving functions later is harder than moving companies.
What are the clinical trial phases, and which teams work on each?
Phase 1 runs in roughly 20 to 100 participants over several months and looks at safety and dosage, with about 70 percent of drugs advancing. Phase 2 runs in up to several hundred patients over several months to two years on efficacy and side effects, and about 33 percent advance. Phase 3 runs in 300 to 3,000 patients over one to four years, with 25 to 30 percent advancing. Phase 4 follows approval in several thousand patients. Clinical pharmacology and operations dominate phase 1, clinical development and biostatistics phase 2, operations and data management phase 3, and pharmacovigilance and medical affairs phase 4.
Mid-Level
What are the best mid-level roles in clinical development and operations?
Clinical research associate is the pivot role, because monitoring sites on a sponsor's behalf teaches you where trials actually fail and makes you employable at sponsors, CROs and sites alike. From there, clinical trial manager is the first job with a budget and a forecast you have to defend in front of other functions. Data management and biostatistics are the quieter route, and they age well because endpoint definition is the one thing a submission cannot recover from. The Association of Clinical Research Professionals separates coordinator and monitor credentials, which is a reasonable guide to which side you are choosing.
How much do pharmaceutical industry jobs pay, and which functions pay most?
On May 2025 federal medians: biological technicians $57,510, chemists and materials scientists $95,060, medical scientists $103,410, industrial production managers $126,060, biochemists and biophysicists $127,410, and natural sciences managers $167,220. The pattern is that the step from doing the science to leading the people doing it is worth more than any step inside the laboratory. Several high-paying pharmaceutical functions, including regulatory strategy, medical affairs and market access, have no occupation code of their own, so they do not appear in federal data at all and are best benchmarked against the management codes.
How does working in regulatory affairs differ from clinical operations?
Clinical operations is delivery: sites, enrolment, data quality and dates, with success measured in a study that finished clean and on time. Regulatory affairs is argument: what the evidence package has to prove, how the agency is likely to read it, and what the label will say. The clock is different too. Operations lives inside a phase that can run one to four years; regulatory lives against a filing and then a review that takes six to ten months once accepted, with priority review compressing the agency's goal to six. Operations rewards logistics, regulatory rewards reading.
How do you choose between discovery, development, manufacturing and commercial?
Ask which failure you would rather own. In discovery the failure is scientific and frequent, and a doctorate is typical entry. In development the failure is a missed endpoint or a slipped date, and the work is coordination under a protocol. In manufacturing and quality the failure is regulatory, which is why CGMP non-compliance makes a drug adulterated by law, and why the authority arrives early. In commercial and medical affairs the failure is external and visible, and promotion is policed: FDA reviews advertising and promotional labeling to confirm it is truthful, balanced and not misleading.
Is the RAC certification worth it, and which clinical research credentials matter?
The Regulatory Affairs Certification is the one credential with real recognition in this industry, in separate RAC-Drugs and RAC-Devices designations. You can sit it with a bachelor's plus three years of regulatory or regulatory-related experience, a master's plus two, a doctorate plus one, or ten years of experience and no degree. On the clinical side, ACRP offers CCRC for coordinators, CCRA for monitors, CPI for investigators and the broader ACRP-CP, with project management and medical device specialties layered on top. Neither is a hiring requirement, and both are cheap evidence you learned the rules deliberately.
How do you prepare for a pharmaceutical industry interview?
Be able to walk the pipeline and name the documents, not only the phases: protocol, clinical study report, the new drug application and its proposed labeling. Know which guidance governs your function and whether it is draft or final, since ICH E6(R3) became final FDA guidance in September 2025 while the artificial intelligence guidance is still a non-binding draft. Prepare one story about a deviation or a finding and what you changed structurally afterwards. And prepare one about a date that moved, with the number in it, because every panel is checking whether you escalate early.
What does a typical day look like for a clinical research associate?
Most of it is spent either preparing for a site visit or recovering from one. On a monitoring day you review consent documentation first, then verify source data against case report forms for the subjects you selected, work through protocol deviations with the coordinator, and check drug accountability and temperature logs, which is where a surprising share of findings originate. Off site, you write visit reports, chase open queries and brief the trial manager on sites you no longer trust. The role is unusual in that its value lies in finding problems, so the good practitioners are the unpopular ones.
Senior-Level
What skills do employers expect from senior pharmaceutical professionals?
Three that are hard to fake. Owning an evidence argument end to end, meaning you decide what the package has to prove rather than draft it, since a new drug application must show safety and effectiveness in the population studied across every dataset, the labeling and the directions for use. Agency interaction, including answering questions on existing data, agreeing to additional studies, and performing in front of an advisory committee that includes a patient representative. And inspection leadership, because FDA inspects facilities worldwide and continuous defensibility cannot be assembled in a week.
How do you move from a functional role into programme or portfolio leadership?
By demonstrating judgement about things outside your function, in writing, before anyone asks. The practical route is to take the cross-functional artefacts nobody owns: the integrated development plan, the inspection readiness position, the evidence gap analysis against a likely payer question. Programme leadership is bought for subtraction as much as delivery, so a documented recommendation to stop something, with the probability of success and the opportunity cost in it, is worth more than three studies delivered on time. Expect the move to cost you technical depth, and decide in advance whether you mind.
What career options exist outside large pharmaceutical companies?
Contract research organisations and contract manufacturers, which need the same regulatory, quality and operational seniority and often pay for breadth. Regulatory consultancies and medical communications agencies, where submission and publication expertise is the product. The agencies themselves, since FDA's own structure, from the Office of New Drugs to the Office of Pharmaceutical Quality to the Office of Surveillance and Epidemiology, is staffed by people with industry backgrounds. Payers, health technology assessment bodies, specialty and generics manufacturers, investor-facing diligence work, and academic trial units. The regulatory and quality skills are the most portable of the set.
How is AI changing drug development, regulatory submissions and pharmacovigilance?
Unevenly, and least where the headlines point. Discovery has used computational methods for years and the binding constraint there is biology. The visible change is in the document layer, because clinical study reports, protocols, patient narratives, CMC sections, agency response drafts, literature screening and trial master file completeness checks are templated and evidence-bound, which is what these models handle well. Pharmacovigilance case intake and coding is the other concentration. The value is shifting from producing a document to verifying it, and from following guidance to being the person who read it when it published.
What does the FDA expect you to prove before using an AI model in a submission?
That the model is credible for a specific context of use. FDA's draft guidance from January 2025 on artificial intelligence supporting regulatory decision-making for drug and biological products sets out a risk-based credibility assessment framework built around exactly that: define the context of use, assess the risk the model carries, and document credibility in proportion to it. It is a Draft Level 1 guidance and explicitly non-binding, so treat it as the agency's current thinking rather than a rule. Alongside it, EMA and FDA jointly issued ten guiding principles for AI in medicines development on 14 January 2026.
How are Medicare drug price negotiations changing pharmaceutical careers?
They are pulling payer reasoning into decisions that used to be purely clinical and regulatory. The first negotiation cycle selected 10 Part D drugs with maximum fair prices effective 1 January 2026, the second selected 15 more effective 1 January 2027, and the third selected 15 drugs covered under Part B and Part D plus one for renegotiation, with prices beginning in 2028. For careers, that moves market access and health economics upstream into indication selection and lifecycle planning, and it makes the ability to argue both the science and the price unusually valuable at senior level.
How do restructuring and portfolio resets affect job security in pharma?
They are the main threat to a pharmaceutical career, and they are driven by pipeline economics rather than by technology. The arithmetic is brutal on its own: about 70 percent of drugs clear phase 1, roughly 33 percent clear phase 2, and 25 to 30 percent clear phase 3, so programme termination is normal rather than exceptional. The defence is function-specific depth plus a credential that travels, because regulatory, quality and clinical operations expertise is bought by sponsors, contract organisations and consultancies alike. Attachment to one molecule is the risk; attachment to one company is a version of it.
Get Tomorrow's Pharma Briefing
BioPharma Dive reaches over 200,000 industry readers each weekday and The Readout puts STAT's biotech desk in the same inboxes as your competitors' teams. When a readout drops, the people across the street have already read three takes on what it means for your program.